
India is facing a multi-faceted public health crisis: acute rural hospital bed deficits, overwhelming out-of-pocket medical expenses, and a surging non-communicable disease burden. Explore systemic solutions for universal, dignified healthcare access.
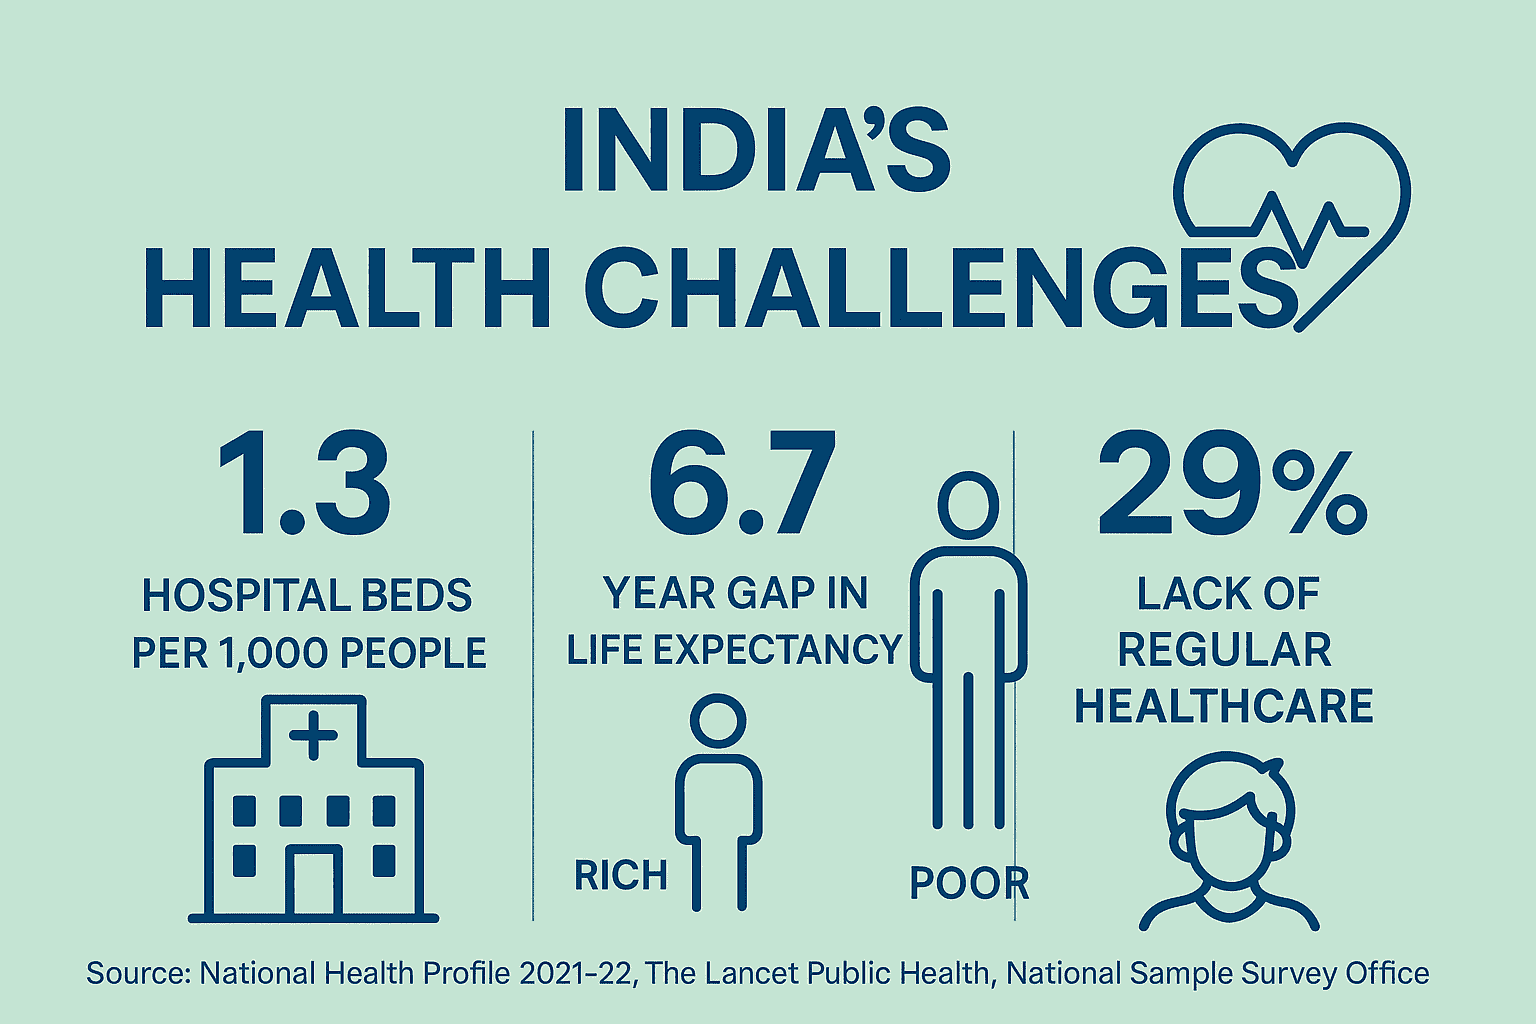
In the world’s most populous nation, good health cannot remain an expensive luxury reserved for urban elites; it is the fundamental bedrock of human dignity and sovereign economic vitality. Yet, across rural India—where nearly 65% of citizens reside—public healthcare infrastructure remains chronically stretched, with just 0.5 government hospital beds per 1,000 people and families bearing over 60% of medical costs out of their own pockets. Addressing India’s healthcare deficit is no longer merely a budgetary debate—it is an urgent humanitarian imperative that cannot wait.
-
Severe Bed Deficit: India maintains just 0.5 government hospital beds per 1,000 citizens—far below the WHO standard of 3 beds per 1,000. -
Catastrophic Expenses: Over 60% of national healthcare spending is paid directly out-of-pocket, pushing 55 million Indians into poverty yearly. -
Urban-Rural Divide: 75% of doctors and 80% of health infrastructure reside in cities, serving just 35% of the total population. -
Community-Led Prevention: SSF combines mobile diagnostic health screening, nutrition camps, and rural wellness education drives.
The Anatomy of the Crisis: India’s Healthcare Infrastructure in Numbers
Public healthcare in India has long been underfunded, hovering at around 1.3% to 1.5% of GDP for decades. This persistent fiscal under-investment manifests directly in severe physical shortages across the healthcare delivery chain, particularly at the primary and secondary levels in rural districts.
Health is not merely a commodity bought in tertiary hospitals; it is a fundamental human right rooted in clean water, early nutrition, and dignified local care. No family should ever be forced to choose between the life of a loved one and financial ruin.
— Shail-Satya Foundation Public Health Initiative
Four Critical Dimensions of the Healthcare Crisis
Understanding the healthcare challenge requires examining the structural bottlenecks that prevent equitable medical delivery across India:
Thousands of rural Primary Health Centres (PHCs) lack 24/7 electricity, basic diagnostic blood analyzers, essential emergency medications, and labor rooms.
High costs of specialized inpatient care, branded pharmaceuticals, and private diagnostics push over 50 million citizens into acute poverty each year.
A rapid epidemiological surge in non-communicable diseases (diabetes, cardiovascular disease, hypertension) superimposed upon persistent infectious ailments.
A chronic shortage of oncologists, pediatricians, surgeons, and psychiatrists outside metropolitan zones, leaving rural patients without specialized care.
Reactive Catastrophic Healthcare vs. Preventive Community Healthcare
Transforming health outcomes requires a fundamental paradigm shift from late-stage emergency response to proactive community wellness:
Reactive Catastrophic Healthcare
- Patients seek medical help only after symptoms become debilitating or terminal.
- Emergency hospitalizations paid via high-interest informal loans or asset liquidation.
- Reliance on unqualified quacks due to remote distances to district hospitals.
- Complete absence of preventive screenings for blood pressure, blood sugar, or cancers.
- Pervasive social stigma surrounding mental illnesses, depression, and adolescent stress.
Preventive Community Healthcare
- Decentralized, routine health screenings catching chronic conditions early.
- Universal financial protection through comprehensive Ayushman Bharat coverage.
- Empowered village wellness centers utilizing telemedicine and digital diagnostics.
- Community nutrition workshops, clean drinking water, and sanitation hygiene.
- Accessible, destigmatized youth counseling and maternal psychological care.
In public health economics, Out-of-Pocket Expenditure (OOPE) refers to direct cash payments made by patients at the point of receiving medical treatment that are not reimbursed by insurance. In India, OOPE exceeds 60% of total health spending—among the steepest rates in the world. According to NITI Aayog and Lancet studies, single catastrophic health emergencies plunge over 50 million Indians into extreme poverty annually, turning illness into a primary catalyst of intergenerational destitution.
The Urban-Rural Healthcare Imbalance
The geographic concentration of medical resources represents one of the starkest structural inequalities in modern India:
- Skued Medical Personnel: Nearly 75% of India’s qualified allopathic doctors and 80% of registered hospitals operate in urban areas, serving only 35% of the total population.
- Rural Healthcare Deserts: Over 65% of citizens residing in villages rely on rural sub-centers and PHCs that often face severe specialist vacancies in surgery, gynecology, and pediatrics.
- Transportation & Lost Wages: For a rural family, accessing a tertiary hospital requires traveling 50 to 100 kilometers, incurring severe transportation costs and lost daily wages before even receiving medical consultation.
- Private Sector Dominance: The retreat or inadequacy of public facilities forces even the poorest rural households to patronize expensive private nursing homes, worsening debt traps.
Actionable Steps to Build a Resilient Public Health System
Achieving universal health coverage and ending medical impoverishment requires targeted policy and community mobilization:
- Increase Public Health Budget to 2.5% of GDP: Fulfill the National Health Policy target to modernize village PHCs, upgrade district diagnostic labs, and guarantee essential medicine stocks.
- Expand Universal Generic Drug Distribution: Scale the Pradhan Mantri Bhartiya Janaushadhi Pariyojana (PMBJP) to ensure quality generic medicines are available at 50%–90% lower cost in every block.
- Deploy Telemedicine & AI Diagnostic Corridors: Utilize the Ayushman Bharat Digital Mission (ABDM) to connect remote village nurses directly with tertiary hospital specialists for real-time consultations.
- Integrate Mental Wellness into Primary Care: Train ASHA workers and community health officers to recognize early depressive and anxiety symptoms, de-stigmatizing psychiatric care at the village level.
Shail-Satya Foundation’s Grassroots Health Initiatives
At Shail-Satya Foundation (SSF), under our Arogya community wellness initiative, we are actively tackling health inequities in rural and underserved communities across Uttar Pradesh and Bihar. We organize regular free diagnostic health camps, provide free foundational health screenings, distribute essential hygiene kits to adolescent girls, and conduct maternal health workshops. By collaborating with local community library hubs, we transform educational centers into community focal points for preventative nutrition, clean water advocacy, and mental wellness support.
Why does India have one of the lowest public hospital bed ratios in the world?
India’s low ratio of 0.5 government hospital beds per 1,000 people stems from decades of public health spending hovering below 1.5% of GDP. Rapid population growth has outpaced public hospital expansion, while private hospital growth has focused almost exclusively on profitable urban centers.
How can out-of-pocket healthcare expenses be effectively reduced for poor families?
By expanding public healthcare funding, providing 100% free generic medicines through government hospitals and Jan Aushadhi Kendras, subsidizing outpatient diagnostic tests, and broadening the coverage criteria of Ayushman Bharat to include outpatient consultations.
How serious is the mental health crisis in India?
India accounts for nearly 15% of the global mental illness burden, with over 150 million citizens needing active psychological intervention. Yet, with fewer than 1 psychiatrist per 100,000 citizens and severe cultural stigma, over 80% of affected individuals never receive professional care.
Can telemedicine solve rural India’s doctor shortage?
Telemedicine bridges the geographic gap by allowing rural nurses and community health officers to connect village patients directly with urban specialists for diagnosis and prescription verification, drastically reducing travel expenses and delays in treatment.
How can individuals get involved with Shail-Satya Foundation’s health initiatives?
You can support our rural medical camps by sponsoring diagnostic supplies, volunteering as medical professionals, donating hygiene kits for young girls, or partnering with our community libraries to organize preventative health workshops.
Healthcare & Epidemiological References
- Ministry of Health and Family Welfare (MoHFW): National Health Profile — Central Bureau of Health Intelligence (CBHI).
- NITI Aayog: Healthy States, Progressive India — Report on the State Health Index.
- World Health Organization (WHO): WHO India Country Cooperation Strategy & Global Health Observatory.
- NIMHANS: National Mental Health Survey of India — Prevalence, Patterns and Outcomes.


